
The walking test tells neuropathy from poor circulation. Nerve pain gets better with walking and is worse at rest and in bed. Artery pain comes on with walking and eases within minutes of stopping.
Both cause foot pain in diabetes. Both are common, and they often show up together. Telling them apart matters because one is treated in a pain clinic and the other can cost you a limb.
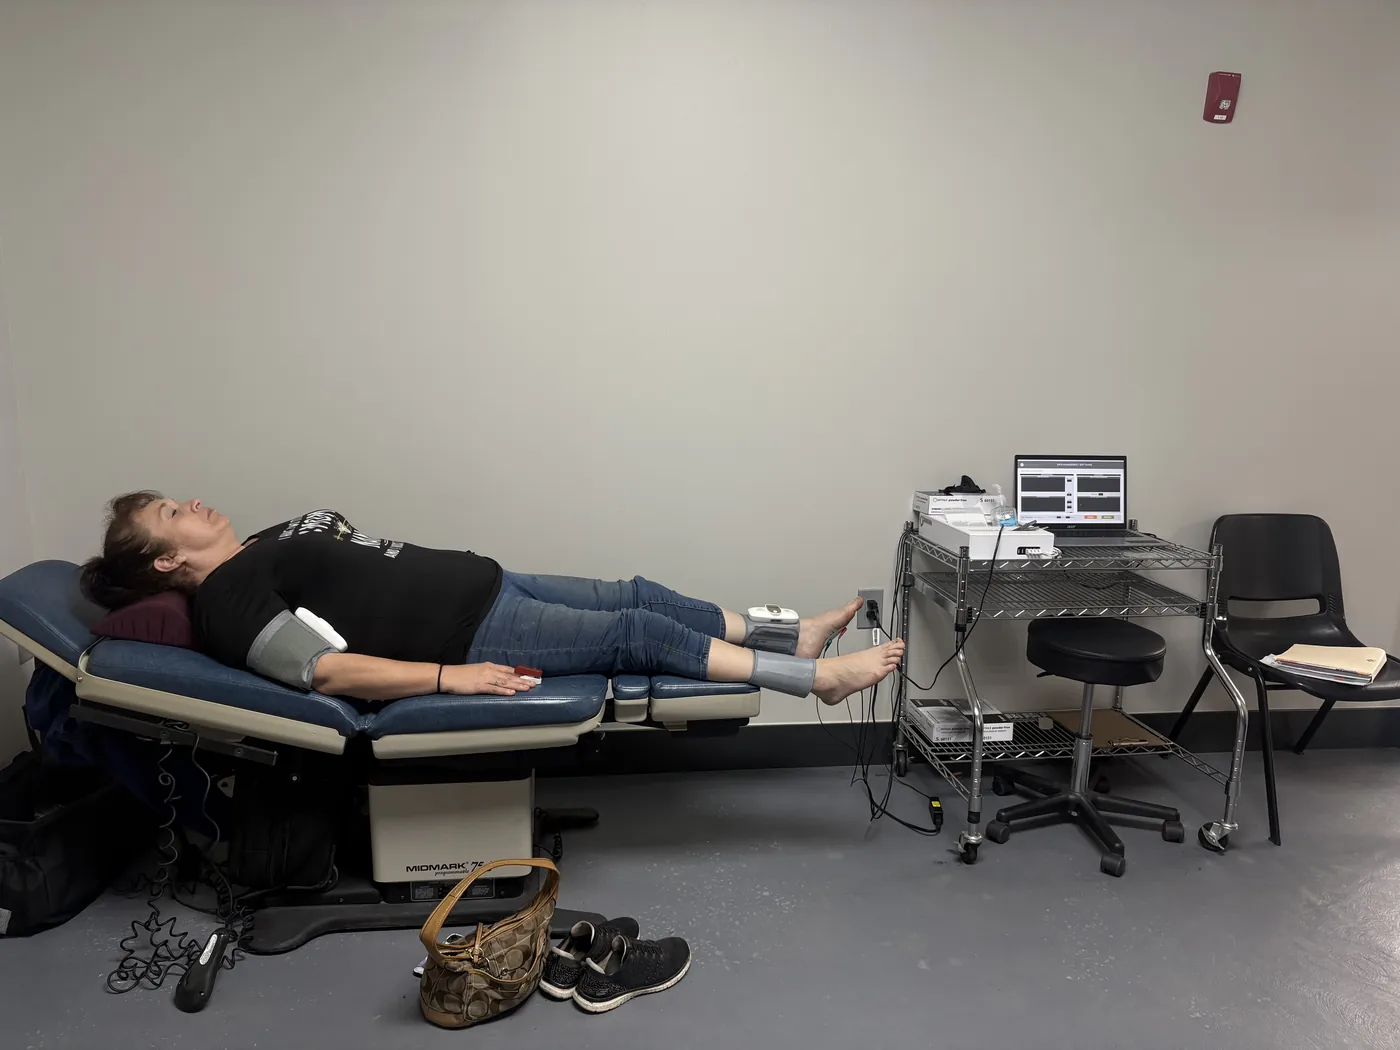
How can you tell neuropathy from poor circulation?
Does walking make it better or worse?
- Better with walking, worse at rest and in bed — that is nerve pain.
- Worse with walking, better standing still — that is artery disease. It is predictable. Pain comes on after about the same distance each time, eases within minutes of stopping, and comes back at the same distance.
That contrast is more reliable than any single exam finding. Patients can usually answer it right away.
What other signs point to nerve damage or poor circulation?
Pointing to neuropathy: burning, tingling, electric or prickling pain; the same in both feet; starts in the toes and climbs; worse at night; skin so sensitive that bedding hurts; normal foot color and warmth.
Pointing to arterial disease: cramping or aching, not burning; often one leg worse; cold, pale or dusky feet; hair loss over the toes and shins; thin shiny skin; nails that thicken and grow slowly; weak or missing pulses; wounds that will not heal.
When to stop reading and get seen urgently
Pain in the forefoot or toes at rest, especially at night, relieved by hanging the foot out of bed — that is rest pain. It signals critical limb ischemia (a leg starved of blood).
A wound, ulcer or blackened area that is not healing.
A foot that is suddenly cold, pale, numb and painful.
Any of those needs a same-day vascular (blood-vessel) exam, not a pain-clinic visit. Mistaking critical ischemia for neuropathy is how limbs are lost.
Why hanging the foot out of bed is such a specific clue
It is the mirror image of nerve pain. In artery disease, letting the foot hang down sends more blood to it. So hanging it down eases the pain, and raising it makes it worse. In neuropathy, position makes little difference. Movement is what helps.
A patient who sleeps in a chair to keep the leg down is describing ischemia. It is worth asking about directly instead of waiting to be told.
Both at once is common
Diabetes damages nerves and arteries in overlapping ways. A large share of patients have some of each. That mix is the dangerous one. Neuropathy takes away the pain that would warn you about an injury from poor blood flow. So the first sign is a wound, not a symptom.
It is also why every exam here checks pulses and skin, not just feeling. Finding neuropathy does not rule out artery disease. Assuming it does is a mistake with real costs.
To be seen, call or text us. We are at 12174 Natural Bridge Rd, Suite 110, St. Louis, MO 63044.
Common questions
Can I have both?
Yes, and in diabetes it is common. The two together are more dangerous than either alone because the neuropathy hides the warning signs of the ischemia.
My feet are cold and burning. Which is it?
Maybe both. Cold feet call for a circulation check. Bring it up directly instead of assuming it is the neuropathy.
What is an ABI?
An ankle-brachial index. It compares blood pressure at the ankle with the arm. It is quick and non-invasive. In long-standing diabetes, hardened vessels can give readings that look better than they are.
Diabetic Foot Care and Preventing Ulcers covers how circulation testing at the ankles decides how much protection a numb foot needs.
Should I see a vascular specialist?
If you have rest pain, a wound that will not heal, or claudication (leg pain when walking) at a predictable distance, yes — and promptly.
Sorting nerve from circulation is one part of the question. If you are also unsteady, see balance and fall-risk assessment.
Sources
- Tehan PE et al. Toe-brachial index and toe systolic blood pressure for the diagnosis of peripheral arterial disease. The Cochrane database of systematic reviews, 2024. PubMed 39474992
- Conte SM et al. Peripheral Arterial Disease. Heart, lung & circulation, 2018. PubMed 29150158
- Mascarenhas JV et al. Peripheral arterial disease. Endocrinology and metabolism clinics of North America, 2014. PubMed 24582096
- McDermott K et al. Etiology, Epidemiology, and Disparities in the Burden of Diabetic Foot Ulcers. Diabetes care, 2023. PubMed 36548709
Hurt in an accident? Start here.
You do not need a lawyer, a police report or a referral to be seen. Bring your symptoms and we will work out the rest.
Monday–Friday, 8:00 a.m. – 4:00 p.m. Same-day appointments are often available for new accident and injury patients.