
A balance and fall-risk assessment measures unsteadiness. We measure every system that causes it: inner ear, feeling in the feet, blood flow, thinking and movement. That is because a fall is almost never caused by just one of them failing.
The fall is a moment. The cascade is the injury.
Most of the harm from a fall is not the fall. It is what follows. First an injury. Then a fair fear of falling again. Then less walking, then less muscle. Then worse blood sugar control and worse blood flow. Then worse nerve function and worse balance, and a higher chance of the next fall. The loop tightens on itself.
What people really lose along the way is not measured in any of that. It is driving. Stairs. Showering without help. Going out in the evening. Staying in their own home. These get given up one at a time, usually quietly. Usually no one in the medical system is told. By the time it comes to light, it comes to light as a broken bone.
The bill does not land only on the person who fell. A working-age daughter cuts her hours. A spouse who was handling their own health problems starts handling two. Someone who drove themselves to visits now needs a ride. They quietly miss the ones nobody can drive them to. Insurance pays without argument for the hip and the rehabilitation, and hesitates over the hour of testing that would have identified the failing component while it was still correctable. Function lost in one home is carried by several.
Three systems hold you upright, and they fail quietly
Balance is a constant give-and-take between three things. The balance organs of the inner ear. Position sense coming up from the feet and legs. And vision. The brain compares all three. Any one of them can slip badly while the other two cover for it. That is why the loss stays hidden until something changes: a dark hallway, a patterned floor, a wet surface, standing up too fast.
So the useful question is not whether you have a weak spot. It is how much backup you have left. Testing one system cannot answer that.

What gets measured, and what each part rules out
- Videonystagmography (VNG) — the inner ear and its links to the brain, read through eye movement. It tells apart an inner-ear loss, which can often be retrained, from a brain pattern that sends the workup elsewhere.
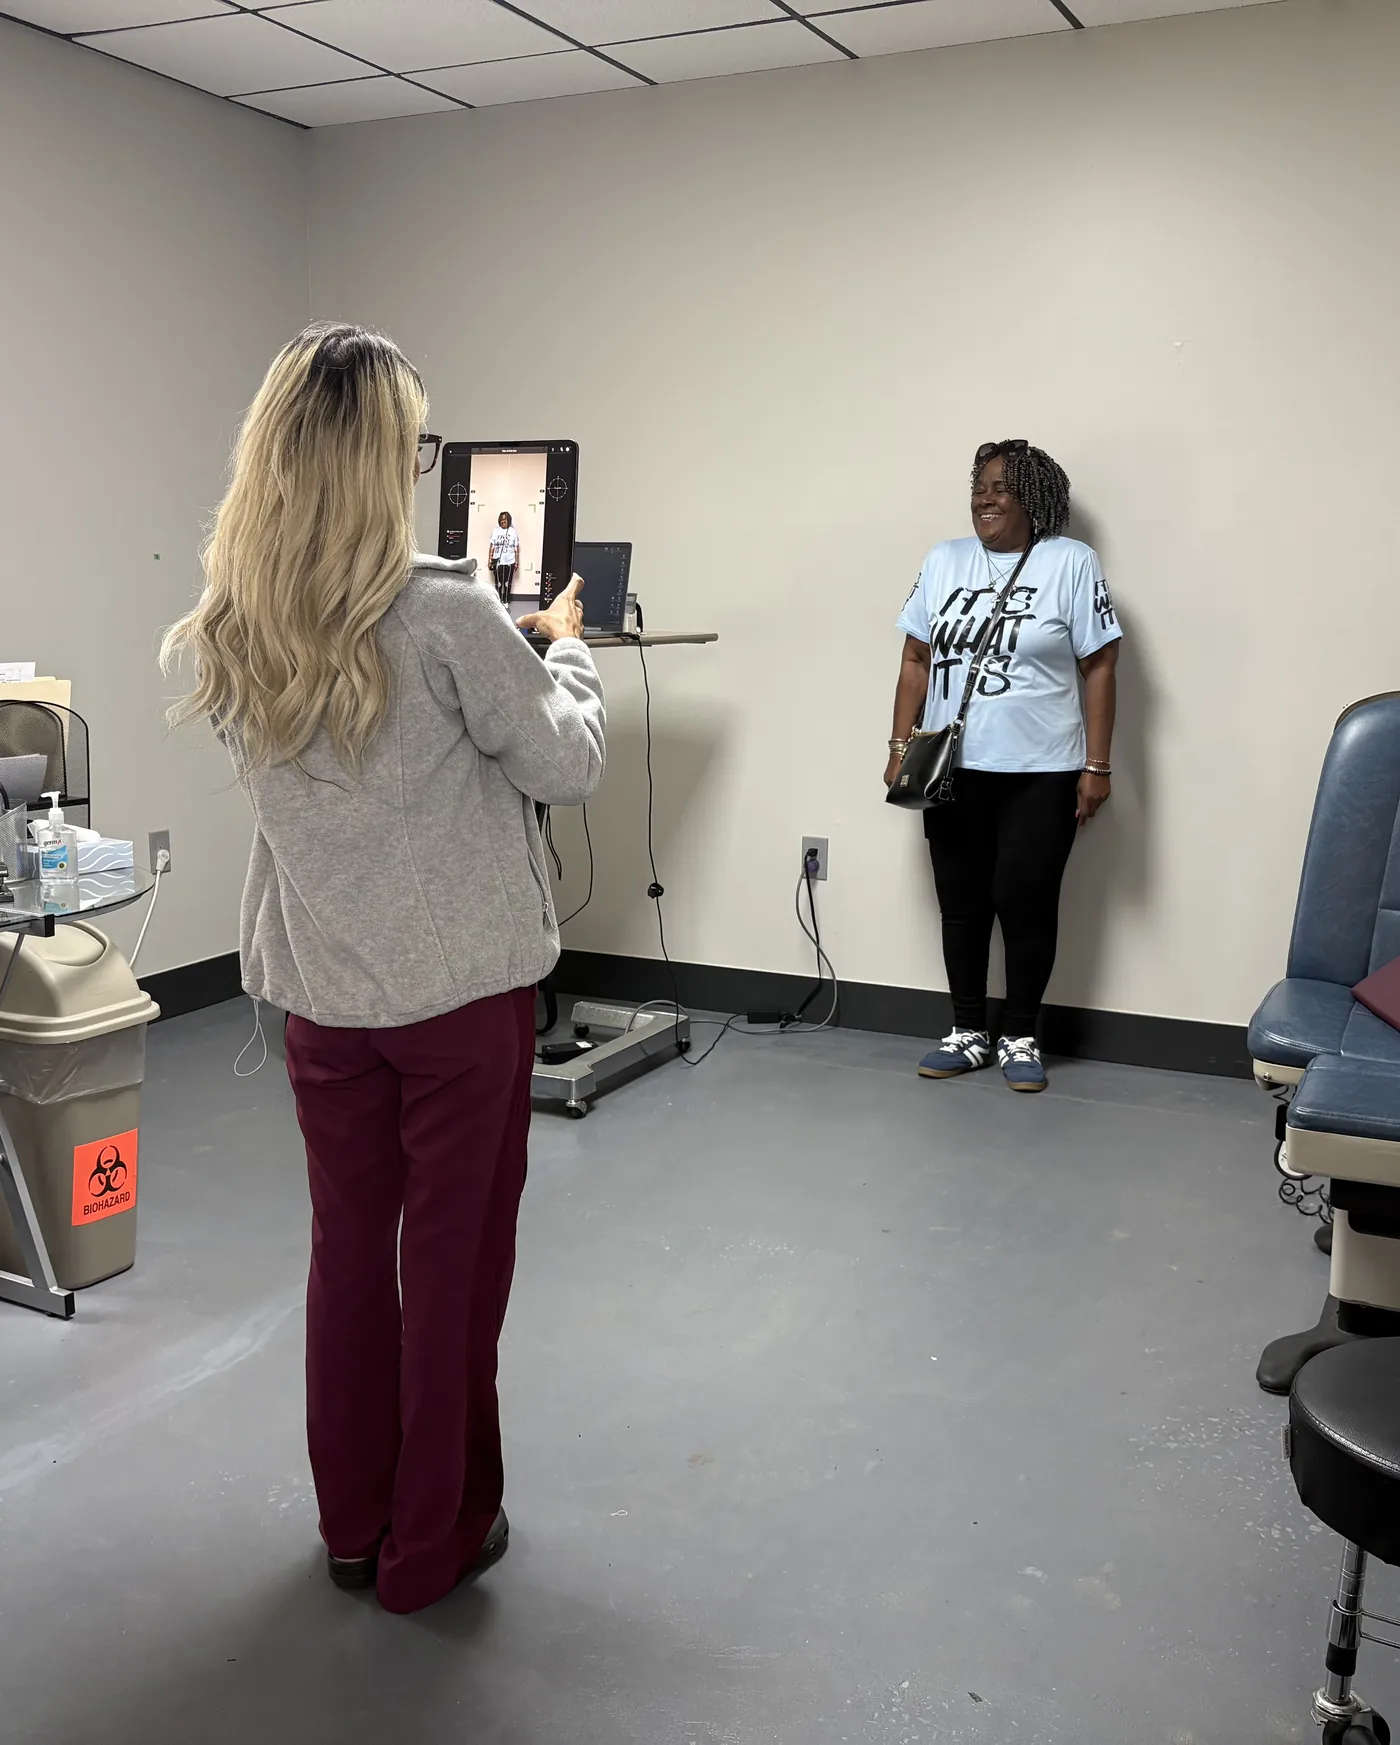
- Kinetisense [Gait Analysis for Fall Analysis] motion analysis — camera capture, with no markers, of how you really stand, shift weight, rise from a chair and walk. It measures the end result, after every system has made up for the others as best it can.
- Cognivue [Cognitive and Memory Testing] cognitive assessment — attention and thinking speed. These decide whether you catch a stumble or just end up on the floor. That is why thinking tests are a standard part of fall-risk assessment.
- Small fiber and autonomic testing — the fibers that carry feeling from the sole, and the ones that hold blood pressure up when you stand. A silent orthostatic drop (blood pressure falling when you stand) causes falls on its own. See small fiber neuropathy.
- Ankle–brachial index and vascular flow — because cold, numb, painful feet are not always a nerve problem. Blood flow and nerves need completely different treatment.
- EMG and nerve conduction studies — where weakness starts. A foot that catches on the carpet can be a nerve in the limb, a nerve root at the spine, or muscle. Only electrodiagnostic testing (electrical nerve and muscle tests) tells them apart. See cervical radiculopathy and spinal stenosis.

Why we assess across disciplines instead of sending you around
Split-up referral is the norm, and it fails this patient. The ear goes to audiology, the feet to podiatry or neurology, the memory to primary care. Three visits, three waits, three reports — and each one fairly decides that what it checked is only mildly off. Nobody is looking at the sum, and the sum is the diagnosis.
How they add up is the finding. A mild vestibular (inner-ear) loss is no big deal on its own. Mild loss of feeling in the feet is no big deal on its own. Slightly slower thinking is no big deal on its own. The person carrying all three at once has almost no room left for error. No single specialist is in a place to see it. That is a flaw in how care is set up. Running the whole assessment under one roof is how we get around it.
Published balance research reaches the same place: a brief test is fine for screening, but a real assessment needs a full set of tests.
The metabolic terrain underneath
Nerve, small vessel, inner ear and brain are not four unrelated organs that fail in the same person by chance. They share a blood supply and the same metabolic base. Small vessels and small nerve fibers feel a metabolic problem first and get checked last. That is how someone is told their labs look fine while three balance systems are already eroding.
So the assessment does not stop at the balance organs. It also covers blood sugar handling and insulin resistance, B12 and vitamin D, blood pressure control, muscle mass and blood flow. That is because these sit upstream of everything the balance tests measure downstream. Insulin resistance runs years ahead of a diabetes diagnosis, and a routine glucose test will not see it. Metformin drains B12. Lost muscle takes two things with it: the strength to catch yourself, and part of the body’s own inflammatory control.
Treating the readout buys time. Treating the terrain changes the direction. See can diabetic neuropathy be reversed.
After a crash, or a head injury
Balance problems after a car crash get blamed on the neck, the concussion, or anxiety. Often they get blamed on whichever was written down first. Any of those may be right. But a crash can also upset the inner ear directly. Post-concussion dizziness, neck injury and inner-ear injury cause overlapping symptoms with different treatments.
Measuring instead of guessing matters more here than almost anywhere else. That is because these cases carry record-keeping stakes as well as medical ones. An objective recording is a different kind of evidence than a description of feeling unsteady. See accident and injury care and post-concussion symptoms after an accident.
What the results actually change
The result is a map of which systems are carrying you and which have stopped. That drives four separate choices. What can be retrained, such as an inner-ear loss, where the exercises match the side and the canal involved. What is medical, such as an orthostatic drop, a shortage of a vitamin, or blood sugar doing damage below the diabetes cutoff. What is structural, such as a nerve root or a stenosis (narrowing) that electrodiagnostic testing has pinned down. And what is about your surroundings, because once we know you are running on vision, then lighting, floor surface and footwear stop being general advice. They become part of the treatment.
We repeat the measurements too, and they are numbers, not hunches — a risk-of-fall percentage, a mobility index, cadence, sway and gait velocity (walking speed). Each is also checked against normal values. One reading is a snapshot. The trend across visits, and whether anything we did bent it, is the part that matters.

Who should be assessed
Anyone with peripheral neuropathy, especially diabetic neuropathy. Anyone who has fallen or nearly fallen in the last year. Anyone with dizziness, lightheadedness on standing, or a lasting sense of being off balance that has never been properly sorted out. Anyone healing from a crash or a head injury. And anyone whose medicine list has grown so long that nobody has lately asked what all of it is doing to their balance.
No referral is required, and we see Missouri Medicaid patients. Call (314) 310-5577 or text (314) 886-5902.
Common questions
Who is this assessment for?
Anyone who has fallen or nearly fallen in the past year. Anyone with numbness in the feet. And anyone who has quietly stopped doing something — stairs, the shower without a rail, walking after dark — because they no longer trust their footing. It is also worth doing after a car accident or a head injury. Then, unsteadiness is easy to blame on the obvious injury and easy to miss. See concussion and head injury.
Does a normal inner-ear result mean nothing is wrong?
No — it narrows the search, which is the point of measuring more than one thing. If the inner-ear recording is clean, the unsteadiness is coming from feeling in the feet and legs, from blood pressure dropping when you stand, from vision, from a medication, or from a nerve root or muscle. Each of those is checked, and each has a different fix. See neuropathy or a circulation problem.
I have neuropathy already. Why test anything else?
Because losing feeling in your feet does not protect you from also losing inner-ear function. In people with diabetes the two show up together often. That is why testing one and stopping there makes the risk look smaller than it is. Balance is a system with backups. What matters is how many of them still work. See peripheral neuropathy.
Is any of it painful?
The balance, motion and thinking parts are not — you sit, stand, walk, and follow targets with your eyes. Nerve conduction studies use brief electrical pulses that feel like a tap. If needle EMG is needed, it uses a fine solid needle. Most people describe a deep ache, not a sharp pain. See EMG and nerve conduction study.
Will the balance testing make me dizzy?
Some position tests can briefly bring on dizziness. When they do, that is a clue, not a side effect. Bringing on the symptom while recording eye movement is how the cause gets found. It usually settles within minutes. Bring a driver if dizziness is your main complaint. See driving when you are not steady.
How long does it take, and do I need a referral?
No referral is needed. The parts can be spread across visits instead of done all at once. That is usually easier if tiredness or pain limits how long you can be tested. Call (314) 310-5577 and we will build it around what you can manage. See Missouri Medicaid (MO HealthNet).
Can any of this be improved, or is it just measuring decline?
A good deal of it is treatable, which is the reason to measure it. Inner-ear losses often respond to focused retraining. Blood pressure that drops on standing, low vitamin levels and blood sugar damage can all be treated. A compressed nerve root can be treated. Strength and gait respond to training. See physical therapy.
Should I bring my medication list?
Yes, all of it, including anything over the counter. Sedatives, some antihistamines, motion-sickness drugs and several blood pressure medicines affect both the recordings and your real-world steadiness. Do not stop anything on your own — bring the list and we will go through it. See prediabetes and nerve damage.
Sources
- de Oliveira Lima RA et al. Efficacy of exercise on balance, fear of falling, and risk of falls in patients with diabetic peripheral neuropathy: a systematic review and meta-analysis. Archives of endocrinology and metabolism, 2021. PubMed 33905633
- Alissa N et al. A Systematic Review of the Effect of Physical Rehabilitation on Balance in People with Diabetic Peripheral Neuropathy Who are at Risk of Falling. Clinical interventions in aging, 2024. PubMed 39050517
- Korkusuz S et al. Balance and gait in individuals with diabetic peripheral neuropathy. Neurological research, 2024. PubMed 37712608
- Elafros MA et al. Towards prevention of diabetic peripheral neuropathy: clinical presentation, pathogenesis, and new treatments. The Lancet. Neurology, 2022. PubMed 36115364
Hurt in an accident? Start here.
You do not need a lawyer, a police report or a referral to be seen. Bring your symptoms and we will work out the rest.
Monday–Friday, 8:00 a.m. – 4:00 p.m. Same-day appointments are often available for new accident and injury patients.